
Sicker Americans More Likely to Misuse Medication

By Pat Anson

What makes someone “misuse” a medication? Does it mean they’re addicted? Are they trying to get high? Do they have a substance use disorder? 

The answer may simply be that they’re sick. 

That’s according to a new study that found that the misuse of prescription drugs is closely tied to the number of chronic conditions a patient has. Previous research has linked chronic pain to higher rates of opioid misuse, but researchers at Syracuse University found the overall disease burden plays a bigger role than whatever medication a patient is taking.

“We talk about the overdose crisis in epidemic terms,” says Andrew London, a Professor of Sociology at Syracuse. “It affects some populations more than others. We wanted to broaden that narrative a little bit and talk about prescription drug misuse more generally, because it’s not just prescription opioid misuse.” 

London and his colleagues analyzed data from the National Wellbeing Survey, an annual survey on the health and well-being of working age adults in the United States.

Nearly 33,000 respondents self-reported whether they were diagnosed in the last 12 months with hypertension, high cholesterol, diabetes, heart disease, obesity or being overweight, chronic obstructive pulmonary disease, post-traumatic stress disorder, traumatic brain injury, depression or anxiety. 

They were also asked whether they misused prescription opioids, tranquilizers, sedatives, or stimulants. Misuse was defined as someone taking a medication that was not prescribed to them or taking it in a way a doctor did not intend, such as taking a higher dose or taking a dose more often than prescribed.

The study findings show that people with no chronic conditions had a 2.8% chance of misusing a medication. The risk doubled to 5.6% for those with one health condition and kept rising from there. People with two conditions have a 8.2% chance, and those with three or more conditions have a 11.7% risk of misuse.

Prescription Drug Misuse by Number of Chronic Health Conditions
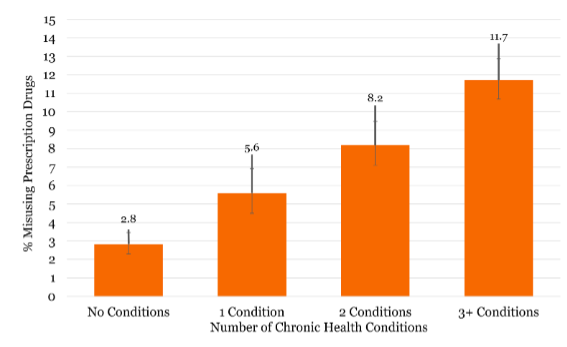
source: SYRacuse university

“This simply tells us that the more conditions an individual manages, the higher the likelihood of misusing medications,” lead author Esther Oshaji, a doctoral student, said in a press release.  

People with anxiety, depression and other mental health conditions reported more misuse than those with physical health conditions, such as obesity or diabetes. Knowing that in advance could help healthcare providers develop more targeted treatments for patients at greater risk of misuse.

“It helps us to know that anxiety and depression are driving misuse among chronically ill patients,” Oshaji says. “Given that it is widely assumed that people misuse drugs because of physical health problems and chronic pain, it is important to show that depression and anxiety are actually driving misuse rates more than physical health conditions.” 

Misuse may also be driven by the number of prescriptions a patient has or the number of doctors they see. People with multiple health conditions generally have more access to medications, and may be more likely to try and manage their symptoms.

“Management of chronic disease requires active decision-making, so people make choices about how they’re managing doctors’ orders,” London says. “We know that patienthood, self-medication and agency are probably part of the story.”

A weakness of the study is that drug misuse is self-reported, and someone may be less likely to admit they misused a medication. Misuse is also a very broad term that includes not using a medication because it’s not effective, no longer needed, or has too many side effects. Simply not taking a drug could be called “misuse.”

Misuse is also frequently confused with abuse, which is when someone uses a substance to get high or for self-harm, leading to negative consequences in life. 

Researchers at Syracuse are now studying whether chronic disease burden is associated with illicit drug use, including marijuana, and whether misuse is associated with gender, age, socioeconomic status and education. 

Hiding Your Chronic Pain Can Backfire

By Crystal Lindell

When I first developed intercostal neuralgia in 2013, I was so undermedicated and in so much pain that hiding my physical deterioration was not an option.

On work trips, I would lay on the floor behind our magazine booth in conference centers crying. Back in the office, I would sob as I typed out emails at my desk.

And I would talk openly with colleagues about wanting to kill myself because the pain was so severe.

It was the same at family events and social gatherings. If I showed up at all, I would lay on a couch in the back of the house for most of the party, tears streaming down my face because I was in too much pain to even sit up right. I would hardly interact with anyone.

And I would openly tell everyone there how I only made it because I took 20 mg of Norco before I left the house — and I’d be taking 20 more in a couple hours.

I was in a lot of pain, and I made no effort to hide that from anyone.

But then, as medication helped me get my pain slightly more under control, and as I learned coping strategies like pacing and forcing myself to stay calm, I started to find it easier to just hide what I was going through.

Unfortunately, I fear I may have now gone too far in the other direction.

The thing is, I saw firsthand how many people recoiled at my pain. They hated it, and by extension, they started to hate me. 

Visible physical pain — especially the kind that never seems to go away — makes people lash out, or worse, pull away completely.

In fact, when you’re in so much physical pain that people are forced to bear witness, they usually decide it’s easier to cover their eyes and pretend you don’t exist.

So, I changed my approach. When I interacted with people in real life, I did my best to pretend to be pain-free.

I loaded up on opioids, anti-inflammatories, and whatever else I could get my hands on, and plastered a smile across my face. I stopped talking about my health issues during polite conversation, and I made sure that if I had tears streaming down my face, it was only after the event, alone in my car.

Unfortunately, I’m sad to report that this has all been extremely effective. People are nicer to me when they think I’m healthy. More professional opportunities have opened up for me. And I have made more friends.

But now, all these years later, I’m starting to wonder if trying to completely hide my chronic pain is also, maybe, a mistake?

Because my chronic pain is very much a part of who I am, and it means that I make heavy sacrifices to show up with a smile on my face.

It means that if I want to get through a 7-hour work shift, I have to sleep for 13 hours before I go in. And then I have to sleep for 13 more when I get back home.

It means that I’m constantly counting out pain pills, and making sure I’m dosing at just the right times so that I’m at my peak when it’s most needed.

It means that a lot of the money I earn is going to medical bills, prescriptions and treatments.

It means that I’m often showing up after being awake all night in pain. And that every hour I give to a colleague or a friend has to be paid for with three hours of rest. 

It means I lose time with my fiancé when I am finally at home, because I physically can’t get out of bed.

Sometimes, I wish I could find a way to explain that to people. I wish I could tell them how much work it takes for me to show up so that they don’t take it — or me — for granted.

Then again, maybe I’m kidding myself in thinking that it even matters. If they really knew how much of a sacrifice I was making to walk through the door, maybe that would just make things worse. It would just make them more uncomfortable, more annoyed, and more avoidant.

I’ve been living with debilitating chronic pain for more than a decade, and I still haven’t found the perfect balance with all this. I still struggle with how open I should be about my health issues, and how much I should hide. 

I still don’t know how to make people understand, or care.

Perhaps I never will. 

In the end, all I can really do is be a person who understands and who cares. 

I have developed a reputation recently for being “super nice” and “caring so much.” I know it’s not always meant as a compliment, but I always take it that way regardless. 

I know what unrelenting pain does to a person, and as such, I also know just how much of an impact it can have when someone, anyone, shows even the slightest bit of empathy for what you’re going through. 

So being nice is the least I can do. 

How the Healthcare System Makes Pain Worse 

By Pat Anson

Do you ever find yourself doing everything right, but never feeling better?

You take your meds, see your doctors regularly, and focus on good nutrition and healthy habits. 

Despite all your efforts, your pain and fatigue never go away. On some days, just getting out of bed or taking a shower is a challenge. You become anxious, depressed. And your mind fills with dark thoughts. 

Will I ever get better? Why am I failing? What is wrong with me?

Millions of people with chronic pain and chronic illness have those same thoughts, and Tamera Lynn Stewart has a message for them: “It’s Not All In Your Head… or Your Body”

That’s the title of Stewart’s new book, which was inspired by her own experiences as a young girl dealing with chronic pain.

“I had a lot of different infections, and was in and out of the hospital when I was young and real little. At three years old, I told my mom that the pain was so bad I just wanted Jesus to take me home. So pain is like nothing new in my life. It has been 24/7 my whole life,” Stewart says. 

Now 45, Stewart has lived through dozens of surgeries and estimates that she’s seen 30 medical specialists. Only in the past decade did they realize that her pain was caused by autoimmune disorders, such as lupus, rheumatoid arthritis, and mixed connective tissue disease. 

Toss in a diagnosis of cervical cancer at age 29 and you have someone who has more than her share of health problems. And a patient who recognized that the U.S. healthcare system often fails the very people it is supposed to help.

“The premise of the book is more about understanding that the systems we deal with, whether it's policy or insurance or the doctors themselves, that they contribute to our pain just as much as our own body. And as much as patients don't like to admit it, sometimes our minds,”  Stewart told PNN.

“The gaslighting that we get from medical providers, insurance companies, whatever, from all of them, that gaslighting turns into depression, second guessing yourself, giving up possibly, or at least slowing down on seeking care. Which then translates into letting our bodies maybe not get the care they need because we quit seeking it, or the depression again keeps us from maybe eating real well, or doing all the other things we know to do. And then you finally go back to a doctor, and they gaslight you again and it starts over again. That's not a way to heal.” 

Stewart likens health to a loop, with your body, nervous system and external systems (insurance, doctors, hospitals, etc.) so connected to each other that you can’t address one without helping or hurting the others.

‘And we get stuck in those loops. I myself am very guilty of that. Got stuck in a ‘I'm never gonna get better’ loop. And then something has to happen to break me out of that. That's where the brain comes in, the mind comes in. For me, spirituality comes in. And until that loop gets broken, it just keeps getting worse. It's like an up-spiral of pain instead of an up-spiral of life,” she explained.

Asked what advice she would give to patients, Stewart has a simple answer: Be direct with doctors. And keep it simple. 

Don’t overwhelm doctors with everything that’s happened to you since the age of 12 (especially on your first visit) and don’t tell them what the Internet diagnosed you with yesterday. Overwhelm a doctor with too many problems, and you’ll be gaslit or sent to a specialist, which means more expenses and more delays in getting treatment. 

“In general, it sounds good that if you have 60 different problems, maybe they'll take you seriously. But I think it's the other way around. I think if you have two or three very significant problems you focus on, I think maybe they're less overwhelmed,” says Stewart. 

Stewart took the lessons she learned as a patient and put them into advocacy. She helped found the P3 Alliance, a patient advocacy group that was influential in getting a law changed in her home state of Oklahoma to better protect patients from opioid deprescribing. The law also gave patients access to their prescription drug monitoring (PDMP) records and strengthened the exemption for treating cancer pain with opioids.

In an age when political parties squabble about nearly everything, Stewart and her fellow advocates were able to get the changes in state law passed unanimously by the Oklahoma House and Senate, and then signed into law by the Governor.

It wasn’t easy, but Stewart says persistence and hard work can be effective in getting government policy changed. And she’s hopeful more patients will get involved in advocacy.

“There's so much more to do. Everywhere, there's so much more to do,” she says.

Congress Needs to Fund Solutions to America's Most Neglected Disease

By Dr. Ilene Ruhoy 

Twelve years ago, I got sick — and no one believed me. Doctor after doctor dismissed my symptoms, writing them off as everything from chronic sinus infections to perimenopause. 

Even as a neurologist, I couldn't get anyone to listen. It took far too long to find the truth: a 7-centimeter tumor was growing in my brain. 

I have never forgotten what it felt like to be dismissed by the very people who were supposed to help me — so now I listen to the patients everyone else has stopped listening to.

That's what brings people from across the country to my office, many carrying the same disease and the same exhaustion of not being believed: Myalgic Encephalomyelitis/Chronic Fatigue Syndrome, or ME/CFS.

The CDC estimates that up to 3.3 million people in the United States suffer from ME/CFS, yet there has been almost nothing done for them, until now.  

The National Institutes of Health approved a clear plan for how to help these patients in 2024: The ME/CFS Research Roadmap. After the November midterm elections, Congress will finish writing the appropriations bills that would fund it. All it takes is $50 million to get started.

ME/CFS is a chronic, multi-system neuroimmune disease. Its hallmark is post-exertional malaise — a severe worsening of symptoms after even minimal physical or cognitive effort — accompanied by autonomic dysfunction, cognitive impairment, chronic pain, fatigue, and immune dysregulation.

There is no FDA-approved treatment and no diagnostic test for ME/CFS. Standard labs and imaging come back normal. For decades, these patients have been written off just like I was, and told the problem is anxiety, stress, or something in their heads.

By the time these people reach me, most have already seen upward of twenty doctors. They arrive expecting to be dismissed, but I refuse to let that happen.

In spending thousands of hours with more than one hundred people living with ME/CFS, I noticed something no one could explain away: these people who had been brushed aside by the medical system were all describing the same disease. They had the same crashes. The same triggers. The same collapse of careers, families, and social lives.

These were strangers scattered across the country. They couldn’t all be imagining the same illness. They are not a mystery to me anymore, but they remain one to the government agencies that fund medical research.

An additional devastating component to ME/CFS is that it completely debilitates some people’s lives without shortening them. People living with the disease can remain bedbound for decades.

But I don’t see this as a tragedy. It’s an opportunity. If we find effective treatments, the people who suffer from this disease today can still be helped.

One thing I’ve come to learn is that their defining symptom is not "fatigue." What these patients experience is an energy mismatch: the body's demand for energy outstrips its supply, and the supply cannot catch up.

My most severely affected patients cannot type for thirty seconds without triggering a crash that sets them back for days. Anyone who has not lived it cannot fathom it — and that understanding gap is part of why the disease has been underfunded.

The research community is ready. I work alongside groups across the country investigating the causes of this disease, and I can tell you what holds them back. It is not a lack of ideas.

Teams are pursuing genuinely novel science. What stops them is money. I know researchers with promising findings who cannot complete their studies because the funds ran out mid-stream. That is the quiet scandal of ME/CFS research: discoveries stall not because the science fails, but because the funding does.

The NIH Roadmap lays out a path forward. The scientific community helped build it. What the Roadmap lacks is an appropriation to match its ambition. Fifty million dollars is a lifeline for millions of Americans, but in the context of the funding bill, it’s simply a rounding error.

The science is ready. The researchers are willing. The patients have waited long enough. It’s time to fund the roadmap. 

Dr. Ilene Ruhoy is a board-certified neurologist trained in environmental toxicology and integrative medicine who has special expertise in chronic and complex illnesses. She has worked with around 100 people living with ME/CFS over her career and has given talks to spread more awareness on the disease. 

Dr. Ruhoy is the author of “Invisible No More” – a practical guide to recovery for patients living with Long Covid and other complex chronic illnesses.


Studies Find Long Term Use of Opioids Ineffective

By Pat Anson

Results from two new studies suggest that opioid pain medication is useful for treating short-term acute pain, but the benefits decline when opioids are taken long term.

In the first study, researchers at the University of Alberta conducted a systematic review of 27 randomized controlled trials of opioids used in the treatment of osteoarthritis or chronic low back pain. Trials were excluded from the review if participants had back pain from surgery, cancer, lumbar spinal stenosis, radiculopathy, sciatica, or rheumatic conditions. 

The study findings, recently published in the British Journal of General Practice, show that opioids work well in the first four weeks of acute pain, but provide little or no benefit if used for longer periods. If taken for more than 12 weeks, researchers say opioids may increase a patient's sensitivity to pain – a controversial theory known as hyperalgesia. 

"If someone breaks a limb, has surgery or a dental problem, where you anticipate the problem is going to resolve in a relatively short time, it's probably OK to give an opioid for that," says principal investigator Scott Garrison, MD, Professor of Family Medicine at the University of Alberta.

"Opioids still have a role in managing acute pain. But if the patient has a condition where this pain is going to be chronic, I think you should reconsider whether you should be offering an opioid, because you may only be giving very short-term pain relief with the possibility of worse pain in the long run, not to mention other potential problems from the opioids."

Garrison and his colleagues made a point of excluding studies from their review if they used a trial design known as "enriched enrollment randomized withdrawal" or EERW. Critics of the EERW method claim it skews data in favor of long-term opioid use.  

While the researchers acknowledge that opioids provide clinically meaningful pain relief for acute pain, they discourage patients from ever taking them. In his own family practice, Garrison says patients refuse to take opioids once he warns them about potential side effects.

"It's very hard to get people off opioids once they have started them, but when patients are given this information about potential harms, they don't want the drug," Garrison said. "Absolutely every patient who is told this up front ends up not taking the opioid. It's so hard to stop, but it's so easy not to start if people are fully informed."

No Changes in Brain Anatomy

The second study also concluded that long-term opioid use does not reduce pain or improve physical function in people with chronic back pain. But the research team at Northwestern University found that long-term opioid use does not cause lasting harm to the brain.

The study compared 70 patients who took opioids for chronic back pain to 70 similar patients who were opioid naive. On average, the opioid group took low to moderate doses for 7.8 years.

The study findings, published in the journal Brain, show the opioid and non-opioid groups reported nearly identical levels of pain, about 5.4 on a zero-to-10 pain scale. The opioid group had slightly worse results for physical function and mental health.

When MRI images were taken of both groups, researchers found little evidence that years of taking opioids altered the brain's anatomy.

"The psychological and brain properties of the participants on long-term prescription opiates were essentially intact," said senior study author A. Vania Apkarian, PhD, director of the Center for Translational Pain Research at Northwestern University Feinberg School of Medicine.

"That's good news because there's this fear nowadays that as soon as you start ingesting opiates, your brain is going to go crazy, and it doesn't," Apkarian said. "But the bad news is that we saw no sign that their pain had gotten any better by using this drug for so many years."

This is believed to be the first study to look at long-term opioid consumption and its effect on the brain. While the MRIs showed no changes in brain anatomy, the images did find differences in the opioid group in how brain regions function and communicate with each other. 

That was particularly true in parts of the brain involved in reward and motivation, suggesting that long-term opioid use may encourage drug-seeking behavior. 

Previous studies of long-term opioid use found that only a small percentage of patients become addicted or abuse their medication and the risk of long-term use is low.

A large study in Australia that followed over 1,500 patients on opioids for five years found that “problematic opioid use” was infrequent. Less than 10% of patients asked for higher doses or for a prescription to be renewed early. By the end of the study, patients were more likely to have stopped taking opioids (20%) than to be diagnosed with opioid dependence (8%).

Do Native Americans Need a Pain App?

By Crystal Lindell

The University of Oklahoma has received a $3.4 million dollar federal grant to help Native Americans with chronic pain – and they’re going to spend all of it on an app.

The money, which is coming from a five-year National Institutes of Health grant, will go towards building the first chronic pain mobile health (mHealth) app designed by and for Native Americans. Nearly one in three Native Americans live with chronic pain, more than any other segment of the U.S. population.

In a news release about the project, the university makes clear the app will only provide behavioral and psychological assistance for pain, because “medications, while commonly prescribed for chronic pain, are also easily abused.” 

Neither of those things are true. Many Americans with chronic pain find it nearly impossible to get opioid pain medication, so they are definitely not “commonly prescribed.” And most pain patients do not abuse their medication.

The researchers referenced our country's history of horrific treatment of Native Americans — including the fact that Oklahoma was the end of the Trail of Tears — to justify this whole endeavor.

“Native American communities have experienced intergenerational trauma, and they continue to experience contemporary traumas,” said Jamie Rhudy, PhD, a professor in the OU Department of Health Promotion Sciences. “These are the types of experiences that can place our brains on high alert and amplify pain.”

It’s infuriating to read that rationale, knowing that programs like this only serve to keep an effective pain treatment away from people who need it: opioids.  

Researchers say the app will focus on things like stress management, anxiety, sleep hygiene, physical health and diet.

“All of these can be drivers and amplifiers of pain,” said Rhudy. Then, in a quote only someone without chronic pain would say, he added this:

“Chronic pain is largely a construct of the brain. We’ve been taught that we have pain because maybe our joints wear out, or we have tissue damage, but everyone experiences pain differently, which our mHealth therapies will recognize and respond to,” said Rhudy.

In short, it’s all in your head.

Then he adds: “Sleep, stress and discrimination are not variables easily targeted by medications, but they do respond well to targeted psychological and behavioral interventions.”

Actually, as a chronic pain patient myself, I can tell you that sleep and stress are both easily targeted by medications. It’s just that many of those medications are controlled substances that have been blamed for our nation’s drug problem.

We asked Tamera Lynn Stewart, an Oklahoma patient advocate, what she thought of the app. She’s glad it's being developed with direct input from Native Americans, but says it “misses the mark pretty badly” in removing barriers they face in getting pain care.  

“My problem isn’t that they’re offering behavioral tools; it’s that we’ve spent years restricting, stigmatizing, or taking away treatments that actually help people, and now we’re approaching an already underserved population with an app while heavily emphasizing discrimination and psychology as drivers of their pain,” said Stewart, National Director of the P3 Alliance, a patient advocacy group. 

“We say they are disadvantaged in receiving quality care for their pain without admitting much of it was caused by the same policies incentivizing this study. All while forgetting to mention that many historical and current drug war policies criminalized or removed the very tools the indigenous population once relied on to treat their pain.” 

Stewart is worried that a pain app designed for a very specific high-risk population will eventually be deployed as a treatment for everyone else – something the pain community has seen before.

“I’m all for adding options. I’m much less enthusiastic when ‘adding an option’ starts looking like another way to redefine the problem so the healthcare system can offer less actual care,” Stewart told PNN.

After building and testing the app, OU researchers plan to have a randomized controlled trial to see how well it works.

“With the team we have in place we’ll be able to bring all the necessary components together to develop, test and deploy a novel, culturally tailored chronic pain intervention that will be scalable,” said Rhudy.

I will definitely be keeping an eye out for the trial results – especially if the app is then pushed on the larger chronic pain community. I’ll be especially interested to see how effective the app is compared to opioid pain medication – although I doubt they will include any data on that.

It’s so disappointing to see money and energy going to projects like this, which are clearly a result of opioid-phobia. Every time a project like this is funded, it means less money and effort going toward interventions that probably have much a higher chance of actually helping people in pain.

Chronic Pain Patients Have Highest Rates of Stigmatizing Language in Medical Records

By Crystal Lindell

Chronic pain patients are the most likely group to find discriminating and judgmental language in their medical records, according to a new study published in JAMA.

The researchers also found that having a low income increased the likelihood of patients finding stigmatizing language in their records. Being older decreased the chances of finding it.

The research is based on a survey of 500 people from a nationally weighted sample of U.S. adults. The study was made possible by passage of the 21st Century Cures Act in 2021, which began a new era of transparency in healthcare by giving patients immediate access to their clinical notes in electronic health records.. 

About 1 in 6 patients (17.1%) reported discriminating or judgmental language (DJL) in their medical records or health care encounters. Such stigmatizing language was defined as any terminology that "conveys disbelief, disapproval, or implicit judgment about a patient’s character, behavior, or social identity.”

Researchers anticipated that medical providers would be more careful about their choice of words, knowing patients might see them. But five years after passage of the Cures Act, there was “little if any improvement” in stigmatizing language.  

“Our findings are consistent with a broader literature on stigma and health communication, demonstrating that DJL can undermine trust, reduce patient engagement, and negatively influence patient perceptions of health outcomes,” wrote lead author Natasha Steele, MD, Stanford University School of Medicine. 

A major limitation of the study is that only 16 of the 500 patients were diagnosed with having chronic pain, a very small sample size. Steele and her colleagues found that those sixteen patients were 3.25 times more likely to find stigmatizing language in their medical notes, compared to people who did not have chronic pain. It was the highest rate of any group in the study.

Low-income patients were 2.64 times more likely to find discriminating and judgmental language, compared to other income groups.

Interestingly, older people were slightly less likely to find stigmatizing language compared to other age groups. For each additional year of age, the odds of finding it dropped by about 2%.

Beyond that, the researchers did not find links between gender, race, ethnicity, or educational level and the likelihood of patients finding stigmatizing language.

Not surprisingly, finding negative language in their medical records made patients less likely to trust that their medical providers were doing a good job of documenting their health issues. 

About 85 percent of patients said they were less likely to see that clinician again and 75% worried it would influence their treatment. A similar percentage thought it would lead to worse health outcomes, including the possibility of medication or diagnostic errors. 

The stigmatizing language was also associated with nearly 6-fold higher odds of diminished trust in clinicians to write accurate and respectful notes.

The researchers said that while health record transparency is a good thing, clinicians need to change their note-take practices in response.

“Our study demonstrates the need for clear standards promoting respectful communication in both medical documentation and clinical interactions. Clinical training programs should emphasize person-centered language, particularly since written notes are increasingly visible to patients, with special attention to populations that may be subject to bias based on social identity,” they said.

Exploring the Connection Between Chronic Pain and Dementia

By Cynthia Toussaint

Difficulty in finding words – also known as “brain fog” -- started for me 30 years ago after I began taking the medication gabapentin for Complex Regional Pain Syndrome. While it initially proved to be effective for me, pulling me out of a ten-year bout of bedridden hell, brain fog was an embarrassing side effect, as I was speaking publicly for HMO reform.

As a spokesperson, having the right word at the right time can make all the difference in “selling” something I’m passionate about. I prayed this troubling symptom would pass as my brain acclimated to gabapentin. It did not.

With time, not only did my brain fog worsen, I started losing thoughts and ideas mid-sentence. Though I could attribute the word loss symptom to gabapentin, my new challenge was something more, something scarier.

Research taught me that long-term persistent pain leads to neural overload and atrophy, literally shrinking parts of the brain responsible for language and memory. Concurrently, I learned that both gabapentin and the clonazepam that I’d been taking for pain and dissociation for four decades worsen dementia symptoms. That was shocking. 

Then in 2014, my mother, a woman grounded in pure love and goodness, but who’d not been herself for a decade, was finally diagnosed with Alzheimer’s disease.

Though Mom wasn’t on any pain meds, she’d suffered since her mid-20s with throbbing varicose veins made worse by failed surgeries.

She also struggled for most of her life with significant low back pain, often eschewing beds for the hard floor. Later, Mom had hip pain severe enough to provoke screams throughout the day. 

I believe my mother’s chronic pain very likely contributed to her dementia development. She’d been dealt a number of other cards that certainly aided the deterioration of her brain.

By the mid-2010s, there were multiple studies linking trauma to dementia. My mom suffered a tsunami of that from her family of origin, her husband, and some of her own children.

lEONA AND CYNTHIA

That trauma produced high levels of toxic stress that led to elevated inflammation, two factors now recognized as drivers of dementia. And she was a woman at an advanced age. Indeed, Mom was a poster child for dementia.

I fear that I may be, too. 

Though for me developing dementia often feels inevitable, being at high risk is not a fait accompli. Regardless of my future’s uncertainty, this I know: I’m not going to just wait for the lights to dim. And I’ll be damned if I suffer the way my beautiful mom did.

For Pain Awareness Month in September, For Grace launched its most personal project in our nearly 25-year history. Named for my beloved mom, “Leona’s Legacy” is a safe, online nurturing space where one can learn about the connection between chronic pain and dementia and how to avoid or, at least, slow down the onset of the disease.

For me, cognitive wellness comes in the form of a plant-based diet, abundant exercise, sleep hygiene, daily meditation, meaningful work, ample reading, and creative therapies like piano, singing and writing.   

But it’s the last pillar of this project that is most meaningful to me, and the closest to my heart. We at For Grace are working on state legislation that, if signed into law, will mitigate financial elder abuse in California.

You see, it wasn’t watching Mom waste away from this wretched disease that was the worst for me. It was what I witnessed during her last ten years, when she lost her capacity for decision-making and was utterly vulnerable to bad players. That’s when she was abused in every way possible by those she loved and thought she could trust.

I know my family’s horror show is far from unique. Elder abuse, in all its forms, is going to become a bigger problem as Boomers age.

Putting a face to the issue, Leona’s Legacy includes touching personal stories from people with pain who have heartbreaking, powerful connections to dementia. Taking a cue from their truth-telling, you’ll also learn about my forthcoming memoir, where I lay bare my family’s multi-generational dysfunction and how I finally broke the trauma cycle for my own survival.

While motivated in part by harm and hurt, the core engine of Leona’s Legacy is the epic love Mom and I shared, unflinching and unbreakable.

I can’t go back and change the abuse she endured, abuse that extended to me, as the family scapegoat, and hastened her death.

But I can still help others in her name.

It is Mom’s enduring love that continues to push me forward, love that will never be forgotten.

Cynthia Toussaint is the founder and spokesperson at For Grace, a non-profit dedicated to bettering the lives of women in pain.

She has lived with Complex Regional Pain Syndrome (CRPS) and 19 co-morbidities for 45 years, and is also a cancer survivor. Cynthia is the author of “Battle for Grace: A Memoir of Pain, Redemption and Impossible Love.”

My Cats Help Me Cope with Chronic Pain

By Crystal Lindell

It is ironic that I was initially opposed to getting a cat because I have chronic pain.

I hate getting up early. I hate having to do anything right when I wake up. And I have no money.  

Cats wake you up at 5 am, expect to be fed immediately, and keeping them alive is expensive.

But when the mother of my fiancé Chris moved into senior housing, she was only allowed to take one of her two cats with her.

Thus, her long-haired tortoiseshell cat – affectionately named Princess Diana – had nowhere to go but to our house.

Although I was initially reluctant, Princess D quickly won me over when, on her first visit, she ran over to me while I was sitting in a rocking chair. She stared up at me with the eyes of a cat looking for love, and jumped up into my lap.  

I was hooked.

We became a one cat household.

Eventually, Princess D’s former sister Basil was also looking for a home, after Chris’ mom was no longer able to care for her either.

CRYSTAL WITH PRINCESS DIANA

Basil, a beautiful long-haired black cat, came with a pre-written warning for the vet, and lots of war stories. She was a scratcher. And a biter. If we hadn’t taken her, they were going to put her down.

Over the years, in the comfort and predictability of our home, Basil has softened. But just last week, she bit my arm because she got confused in the middle of the night.

We love her regardless.

After Basil came to live with us, we found our orange boy Goose and our brown tabby Goldie Hawn, outside. 

And when we moved in with my relatives, two gray-haired cats, Gracie and Cinnamon, joined our crew.

Yes, that brings the total to six cats. Yes, I know that puts me into crazy cat lady territory. But the thing about being a crazy cat lady is that I love them all too much to care what you think.

Just as I feared, they do all wake us up at 5 am, asking for food. And it does indeed feel like I’m pulling myself out of cement to get out of bed, just so that I can open a can of Friskies for them at dawn.

Truth be told though, having a reason – actually six reasons – to get out of bed every morning goes a long way when you’re dealing with pain that never ends. They give me purpose, and in return, I give them treats.

Having six cats also means that at least one of them is always willing to nap with me whenever I’m having a bad pain day. And naps covered in cats are healing. 

I confess, we do spend a lot of our money on our cats, especially after Princess Diana developed diabetes and almost died. We buy $140 vials of insulin every other month to keep her alive.

But she keeps me alive by giving me a reason to live, so really it all evens out.

In the end, our six cats give my life meaning, relieve stress, take my mind off my pain, and fill our home with love. All of those things go a very long way toward helping me cope with chronic pain.

In fact, there’s even data to back this up.  

In 2019, a National Poll on Healthy Aging conducted by AARP and the University of Michigan found that pets can offer their owners a wide range of health benefits.

The people surveyed said their pets helped them enjoy life (88%), made them feel loved (86%), helped reduce stress (79%), kept them physically active (64%) and helped them cope with physical and emotional symptoms (60%), such as taking their mind off pain (34%).

For those who said their health was fair or poor, pet ownership offers the most benefits. More than 70% of older adults said their pet helps them cope with life’s challenges, and nearly half (46%) said their pets help distract them from pain.

I used to think that having chronic pain was why I could never care for a pet. But I’ve come to understand that caring for a pet is one of those things that gives more than it takes. It’s because of my chronic pain, that having a pet – or six of them – is so vital to my well-being.

Less Is More: It Doesn’t Take Much Exercise to Reduce Pain

By Pat Anson

It won’t cure you or make your pain go away, but moderate levels of exercise could give you some relief from acute and chronic pain, according to a new study by Australian researchers.

In a systematic review of 157 clinical trials, a research team at Adelaide University found that less than two hours of exercise a week could reduce pain by about 1.1 points on the zero-to-ten pain scale. In fact, exercise of low intensity and short duration appears to be more beneficial than longer, intense workouts.

“Our study found that exercise was associated with substantial reductions in acute and chronic pain across all forms of exercise – whether that be via aerobic or resistance exercise, or through gentler movement such as yoga, Pilates or tai chi,” lead author Ben Singh, PhD, a Research Fellow at Adelaide’s School of Allied Health and Human Performance, said in a press release.

“Importantly, we found that more exercise wasn’t necessarily better. In fact, shorter-duration and lower-intensity programs showed greater reductions in pain, suggesting people may not need to exercise harder or for longer to experience meaningful benefits.”

The study findings, published in the journal PAIN Reports, show the most significant reductions were for pain caused by these conditions:

  • Axial spondylarthritis

  • Cancer

  • Musculoskeletal conditions

  • Fibromyalgia

  • Hip replacement

  • Low back pain

  • Migraine and headache

  • Neck pain 

  • Osteoarthritis

  • Idiopathic pain in older adults

  • Osteoporosis

  • Menopause

  • Pregnancy-related pain

  • Primary dysmenorrhea

  • Rheumatoid arthritis 

Low intensity workouts from tai chi, yoga and Pilates were beneficial, but the form of exercise that produced the largest reduction in pain was a bit of a surprise: Dancing.

That finding, however, is based on a single study of dancing by fibromyalgia patients and should be taken with caution. “Although dance-based interventions may offer promise for this population,” researchers say further studies are needed to prove the effect.

There are four key reasons why exercise has an analgesic effect.

First, exercise stimulates the release of endogenous hormones (endorphins), which act as natural painkillers and increase pain tolerance.

Second, exercise enhances the production of neurotransmitters such as serotonin and norepinephrine, which play crucial roles in mood and pain modulation.

Third, exercise reduces systemic inflammation, a common driver of chronic pain, by modulating immune system function.

Finally, exercise activates the body’s endocannabinoid system, which helps to modulate pain perception, mood, and inflammation.

“When we exercise, our body releases chemicals including endorphins and serotonin that can help reduce how strongly we feel pain and increase our pain tolerance,” Singh explained. “Additionally, it helps calm inflammation and change the way our brain responds to pain, while also improving mood.

“These effects help explain why exercise can be such a powerful tool for pain management. Yet despite the evidence, it isn’t used as routinely as it could be and is rarely prescribed with the same precision as medication.”

The idea that exercising less than 2 hours a week is more effective runs counter to many current exercise guidelines, which recommend 150 minutes or more per week. That amount can feel unattainable for many people with chronic pain. Shorter, less intense physical activity is more realistic and may help people overcome their resistance to exercise. 

“These findings support starting with manageable, lower-dose (exercise) programs to build confidence, promote adherence, and reduce fear of symptom flare-ups, key barriers for people with chronic pain,” researchers concluded. 

“Exercise should not be considered a universal solution or expected to eliminate pain entirely. Its efficacy will depend on individual factors such as the underlying pain condition, level of physical function, and adherence.” 

Unexplained Chronic Pain Had Me Hoping for Cancer Diagnosis

By Crystal Lindell

Having chronic pain that can’t be diagnosed or explained will take you to some pretty messed up places mentally.

I had my first mammogram this week, and I have to confess something: Part of me was secretly hoping it came back positive for cancer.

It didn’t. I’m fine. Everything was normal.

But the chronic pain I have in my ribs is just a few centimeters under my right breast, so deep down, I was kind of, sort of, hoping that maybe the cause of the pain that’s plagued me for 13 years was actually a slow moving breast cancer the whole time.

I know it doesn’t make a lot of sense. But my pain also doesn’t make a lot of sense.

At least breast cancer would be treatable.

The official medical diagnosis for the pain in my ribs is “intercostal neuralgia,” which is literally just medical jargon that translates to “rib pain.”

Yes, the pain in my ribs is “rib pain.”

There is no cure for intercostal neuralgia. I’ve tried every possible treatment. So now I just manage it with a cocktail of substances ranging from morphine to Advil.

There’s also no official cause, at least not in my case.

The best theory my doctors have come up with is that it’s a delayed reaction to me having my gall bladder taken out in 2008. The only issue there is that I had my gall bladder taken out five years before the pain suddenly started in 2013.

Taking things one step further, the doctors believe I am more susceptible to intercostal neuralgia because I have hypermobile Ehlers-Danlos Syndrome (EDS). I got that diagnosis in 2018. And so far, that’s as close as I’ve come to anything tangible.

Yes, it was nice to finally have something more specific than “rib pain” to point to. At least there was some sort of underlying cause. 

Finally, my chronic, hard-to-manage, some-days-totally-debilitating pain was kind of, a little bit explained. EDS created the perfect environment for nerve damage to appear five years after my gall bladder surgery.

Fine. Yes. It’s probably that. They think.

None of the doctors will ever say that they know it’s that. It’s all just a theory. There’s no scan that shows intercostal neuralgia, no blood work panel. It’s just their best guess.

The thing is, the pain is so specifically located that I can point to exactly where it is. The best way I know to describe it is that it kind of feels like there’s a jagged marble lodged under my right breast. Sometimes, the marble moves around and ejects a knife further into my ribs, which causes the pain to radiate throughout my entire right torso.

It’s the kind of pain that really feels like it should be caused by something specific, something provable. Something that can be fixed, or at least treated. Something like cancer.

I know how messed up it is to hope for cancer. And I know that if I ever actually do get cancer, I will fully regret these thoughts.

To be honest, I thought my days of hoping the cancer test comes back positive were long gone. After I got the EDS diagnosis, I hoped I could finally just accept my chronic pain fate.

But when I opened my mammogram results on MyChart yesterday, a tinge of disappointment washed over me as I saw that everything was “normal.” 

I realized just how much I still longed for a more tangible diagnosis, and how much I still desperately wished my pain came with some sort of cure.

There is one major upside to all this though: At least I don’t have cancer.

Mourning the Loss of a Healthy Body

By  Li-elle Rapaport 

Body changes can raise disturbing feelings, such as looking in a mirror and seeing a reflection that may feel spiritually empty, unproductive, ugly or weak.

Unpleasant sensations such as pain, pins and needles, soreness coursing through limbs and an inexplicable fog filling the head are a reminder that this body is not the same you anymore, prompting us to wish there was a way to get back there. It may feel impossible to live well unless you do.

This is the disillusionment that most of the population will face at some point in life, through aging, chronic pain or invisible illness (a disease or health problem that cannot be externally seen, including autoimmune diseases, chronic pain and fatigue, and recently, long COVID).

Recent global estimates suggest one in five people are currently experiencing chronic pain. The most prevalent chronic pain reported by adults ages 75 and over includes low back pain and migraine, while tension-type headaches are more often experienced by younger adults. Chronic illness (diabetes, heart disease and other mid-to-late-life diagnoses) affects about three-quarters of the world population.

Despite how common chronic illness is worldwide, the nuances of navigating a changing body are not often discussed. It’s time for an honest, evidence-based conversation about what it means to navigate chronic pain and illness, aging and transforming identity post-diagnosis, and how to grieve this loss and maintain meaning through these changes.

Why It Matters

Research suggest that those with internalized stigma of chronic illness are more preoccupied with how their illness detracts from their view of themselves, and also have a greater tendency to overlook positive aspects of life with a chronic illness.

Psychologists have observed how preoccupation with illness or pain is often accompanied by other grief behaviours. A 2025 study explored how Danish chronic illness patients navigated loss and growth. The study found that many with chronic illness find themselves mourning the life that they thought they would have, often leading to loss of motivation and joy in everyday life.

The perception of losing the life they had once envisioned is often accompanied by a focus on getting back to the “before illness” version of themselves as people struggle to accept how their body has changed, perhaps in how it looks but definitely in how it feels.

These changes and associated feelings of loss often permeate a person’s sense of identity, as well as their perceived roles within social relationships. Many report a fear of burdening others, especially loved ones, often describing feelings of guilt that “others have it worse than I do.” This is where internalized stigma festers.

Some people have also described feelings of anger, isolation, shame and exhaustion accompanying sadness. Meanwhile, others have expressed frustration over a gradual loss rather than a “clean break,” accompanied by the inability to find closure.

Making Sense of Grief

First, it’s important to understand why accepting this continuous loss feels so impossible. Theories of control in psychology state that humans desire control or the ability to achieve a desired outcome according to our own standards.

When that ability is seen as stripped away, people are more likely to experience negative mental health symptoms, like anxiety, depression and even grief. Specifically, feelings of diminished perceived control (subjective belief about our ability to achieve desired outcomes) occur when we face continuous roadblocks to living our desired life because of chronic illness.

One of the major consequences of loss and major life change is that it can disrupt meaning and challenge identity, purpose and assumptions about the future. At a time when people feel there is little they can control, psychologist Robert Neimeyer’s Meaning Reconstruction Theory poses the questions: “How do I move forward?” and “What matters most?”

While the original theory was proposed as an approach to coping with the loss of a loved one, the process is somewhat similar to grieving the close ally that is your body. This theory approaches grief by making sense of the loss and finding ways to rebuild a sense of purpose in a changed life (and body).

To answer relevant questions about how to move forward with chronic illness, two ongoing approaches are needed: integrating the loss and recentring purpose and meaning.

Integrating the loss may look like processing significant bodily losses in therapy, finding trusted loved ones to talk about the loss with and focusing on being realistic about your current body without judgment.

Second, recentring purpose during this major life change involves understanding your why: why is this loss so significant to you, why does it hurt? Maybe it’s because you love hiking in the mountains and a new diagnosis with arthritis feels like the end of this joy. Part of rebuilding meaning is finding new approaches to fulfilling this purpose — perhaps hiking may look different, but nature can be accessed and loved with chronic illness present.

Rebuilding meaning might also look like making meaning from this loss: What has this change taught you about yourself, about the impact you can make? Approaching present and future with this perspective helps process grief in a more protective way.

Living with chronic pain, illness and the changes that come with aging often involves grieving physical loss, but also shifts in purpose, relationships, identity and future plans. While these changes challenge our perceived control and purpose, the Meaning Reconstruction Theory suggests that acceptance and growth comes with integrating loss and rebuilding purpose alongside these changes.

Although the present is different than anticipated, fulfilment is still possible with your current body.

Li-elle Rapaport is a therapist and doctoral candidate in the Department of Psychology, University of Manitoba

This article originally appeared in The Conversation and is republished with permission. 

I May Not Look Like I’m in Pain – But I Am

By Crystal Lindell

When my mom had a sudden perforated ulcer in her stomach in 2022, she fell to the ground at work and was taken to the hospital via ambulance. While waiting in the ER, she alternated between the floor and the bed in eerie silence.

She didn’t scream, she didn’t cry. She just stayed quiet while waiting for help. 

My mom had been dealing with a very bad hip for years, so extreme pain wasn’t new to her, and she had long ago trained her mind and body to stay calm when she was in pain.  

However, because she wasn’t screaming at the top of her lungs, all the nurses assumed she was fine.

It took the staff 9 hours to finally order a cat scan, which showed the hole in her stomach. They immediately rushed her into emergency surgery, which barely saved her life.

Perhaps I inherited some of that ability to be quiet anytime my pain flares up. But I think it’s more likely that I learned what anyone who’s dealt with pain for long periods of time knows: The worst thing you can do is scream.

That does not align with the common media portrayal of pain though. In movies and TV shows, extreme pain involves obscene levels of screaming, buckets of tears, and facial expressions that actually match the number 10 emoji on the pain scale.

The patient we see in the media always has the vibe of a screeching red fire alarm.

In real life though, that’s not what extreme pain always looks like – at least not for chronic pain patients.

In real life, deep, unrelenting pain often arrives with a scary level of calmness, an odd silence, and maybe – on the especially bad days –  a few quiet tears streaming down the face.

Unfortunately, this disconnect between how pain is portrayed vs. what it actually looks like can lead to some very upsetting consequences. If you’re not screaming at the top of your lungs when you’re in pain, then everyone assumes you must be faking it.

By everyone, I don’t just mean friends and family – I also mean important people like bosses, clients, and even doctors.  

There are two main reasons why living with chronic pain usually changes how you react to level 11 pain flares.

One, you realize pretty quickly that staying calm is the best way to keep the pain from escalating even higher. 

And two, our vocal chords just aren’t designed to scream at full volume for very long.

Even though I have some days where the pain drops down to as low as a 2 or a 3, I spend most days trying to keep level 7-9 pain from ruining my life. 

I take multiple substances to try to accomplish that, but still spend lots of time coping with pain levels that healthy people would probably go to the ER for.

The reality is that it just isn’t physically possible for me to scream at the top of my lungs until the pain subsides. It would be like having the fire alarm go off every single day.  

Eventually, you realize that the only thing the alarm was doing was making things worse. 

All this means that most of the time, you aren’t able to tell if someone is in pain just by looking at them. In fact, it’s the people in the most pain who are often the best at hiding it.

As such, the best way to handle the situation as an outsider is this: If someone tells you they are in pain, believe them. 

It really is that simple. 

Researchers To Use AI to Study Chronic Pain in Rural Older Adults

By Crystal Lindell

Virginia Tech researchers will receive nearly half a million dollars from the federal government to use artificial intelligence (AI) to study chronic pain in older adults living in rural areas.

The study is being led by Huaiyang Zhong, PhD, an Assistant Professor in the Grado Department of Industrial and Systems Engineering at Virginia Tech. He was awarded a $460,260 grant from the National Institute on Aging.

People in rural areas have significantly higher rates of chronic pain than those who live in big cities. They’re also at a big disadvantage when it comes to getting their pain treated, due to the distances many have to travel to see a doctor. 

Zhong and his team hope AI can help improve pain assessments and clinical decision making by doctors, with the goal of reducing pain and pain-related complications in older patients.

“I became interested in chronic pain because it's incredibly common, but also incredibly complicated,” Zhong said in a press release. “Pain is not just a single diagnosis, and it's not a number on a scale like a lot of medical diagnoses. Pain itself can affect mobility, mental health, sleep, cognitive functions, and overall quality of life. It's a multidimensional thing.”

Zhong hopes to learn how chronic pain evolves, which patients are more vulnerable to poor outcomes, and how healthcare systems can treat them more effectively. 

It all starts with the information that is sometimes buried in clinical notes. Researchers will use machine learning and natural language processing to analyze patient records and create “risk dashboards” to help doctors recognize when a patient is at risk of complications, such as depression or cognitive impairment.

“I ultimately want to help clinicians move toward more personalized pain management,” Zhong said. “This means understanding not just how much pain somebody has, but the broader health context surrounding that pain.”

Zhong is not a medical doctor, but has a PhD in Management Science and Engineering from Stanford University. He thinks his background in industrial and systems engineering (ISE) can help solve complex healthcare problems. 

“Machine learning can tell us which patients are at elevated risk, but as ISE researchers, we ask the next questions: What should we do with that information? How should limited healthcare resources be allocated? How does this information feed into clinical workflows? How does using this actually improve clinical outcomes?” Zhong said. 

Robert McNamara, PhD, a clinical psychologist and Associate Professor in Virginia Tech’s  School of Medicine, is a collaborator on the project. He looks forward to investigating the medical problems faced by rural older adults with chronic pain.

“We foresee this work leading to early, actionable insight for providers in rural areas, enabling appropriate intervention and referral, and ultimately improving quality of life for this vulnerable population,” said McNamara.

As a rural resident myself, who also suffers from chronic pain, I am always glad to see more resources going to research like this. It will be interesting to see if AI is actually able to offer new insights. 

Many of the older adults I know in northern Illinois who have chronic pain already know how to improve their healthcare and quality of life. First and foremost, they want access restored to opioid medication. 

There’s also a high need for making telehealth doctor appointments easier for older adults to access. In-home care is another high priority. It’s a chore to go to a doctor who might be a two-hour drive away. If there was a program where a traveling doctor could come to a rural community for a day, that would be a massive help.

Hopefully, AI offers real, practical insights into these types of problems, and all the other issues rural chronic pain patients suffer from.

How I’m Able to Work Again with Chronic Pain

By Crystal Lindell

How do I do it?

On my days off, I sleep for 15 hours, waking up only to eat and pet my cats.

I can’t get out of bed without Norco, morphine, Advil, 7-OH, and Tums.

And I have a super supportive partner who does all the house work, all the grocery shopping, and changes all the litter boxes.  

That’s the short answer for how I manage to work a full-time job outside of the home while living with debilitating chronic pain. It takes a lot of drugs, a lot of sleep, a lot of support, and a lot of luck.

I also eat the same meals nearly every day to make food prep and decision-making easier. And I make zero plans for days off.

I started working again in April – my first full-time job in over four years. 

Despite my years of experience as a professional journalist working in the corporate world, I took a job as a gas station cashier close to home. I was fed up with corporate culture and just wanted to see if I could even handle working full-time again in any capacity with my health issues.

I also needed health insurance and the gas station offered me that after just one month.

Now that it's been a little over three months, it felt like a good time to reflect on how it’s going.

To be honest with you, I absolutely love it!

I love going to work every day. I love interacting with the public and making friends with my co-workers. I love getting out of the house. And I have already been promoted to the first level of management, with hopes of continuing up the ladder.

But it has taken a major toll on my body. 

I wake up in so much pain that walking to the bathroom feels like I’m using muscles for the first time in years. And after my shifts, I only have enough energy to change out of my work clothes and get into bed. 

I really don’t know if I’ll be able to keep it up if 7-OH is officially made into a Schedule One controlled substance.

I really, really want to keep it up though. 

I want to keep working, being good at my job, and forming surprisingly deep connections with my fellow employees. I want to keep feeling productive and living like I have a purpose in this world – even if that purpose is just helping truckers get back on the road.

That’s because, despite all the stereotypes about people with chronic illnesses, I desperately want to work. 

In reality, it’s the people constantly trying to take away my access to opioids and 7-OH who want me to be unemployed and bed bound. 

They may soon get their wish if 7-OH is banned – a policy being pushed in the name of “protecting me.”

Protection I do not want and didn’t ask for.

If it happens, the anti-7-OH advocates and federal health officials won’t take any responsibility. They won’t even offer me health insurance. Instead, I suspect they will tell me to go out and get a job.




